National HIV/AIDS and Aging Awareness Day: HIV Aging Care Bronx Support at Hope Center

One national figure keeps stopping me. More than half of Americans with diagnosed HIV have already passed 50, according to HIV.gov. New York City’s 2024 estimate for that age group was 49,400.
The Bronx number is its own story. About 25,500 borough residents were living with HIV across all ages, and its rate of new diagnoses remained the city’s highest. Meanwhile, the person behind the count may be managing good HIV treatment, diabetes, heart disease, arthritis, pain, a wound and an old stroke, all before lunch. Tuesday’s medication pass can say rather more than an awareness-day poster.
HIV Aging Care Bronx Begins With Medication Continuity
Every medication routine has a weak seam. A transfer can expose it. So can nausea, a swallowing problem, a changed order, a confusing discharge list, or one bottle that never arrived.
On admission, somebody has to play detective. When was the last dose? What was actually taken at home? Does anything on today’s list clash with the bottles or records from yesterday? Allergies enter the discussion, then kidney and liver function, then the latest viral-load and CD4 information. The prescriber may change the plan. Otherwise, the established HIV schedule keeps moving.
Now open the rest of the drawer. Blood-pressure pills. Pain medicine. Vitamins from home. Perhaps an herbal product nobody thought counted as medicine. Federal HIV guidance calls polypharmacy common in older adults and asks clinicians to review the whole collection regularly. Interactions are one worry; dizziness, duplication and a routine too complicated to follow are others. Pharmacy sees one angle, nursing another. They need to compare notes.
More Than One Diagnosis Usually Walks Through the Door
The chart may say “HIV” near the top. By lunchtime, blood pressure, blood sugar, pain, appetite and gait may be driving the day.
Heart disease comes in from one direction, fragile bones from another. Memory can be changing too. Federal HIV guidance does not invent a parallel aging system; it begins with the screening older adults generally receive and asks clinicians to read the results alongside HIV history and other risks. That sounds tidy on paper. The resident using the walker is less tidy.
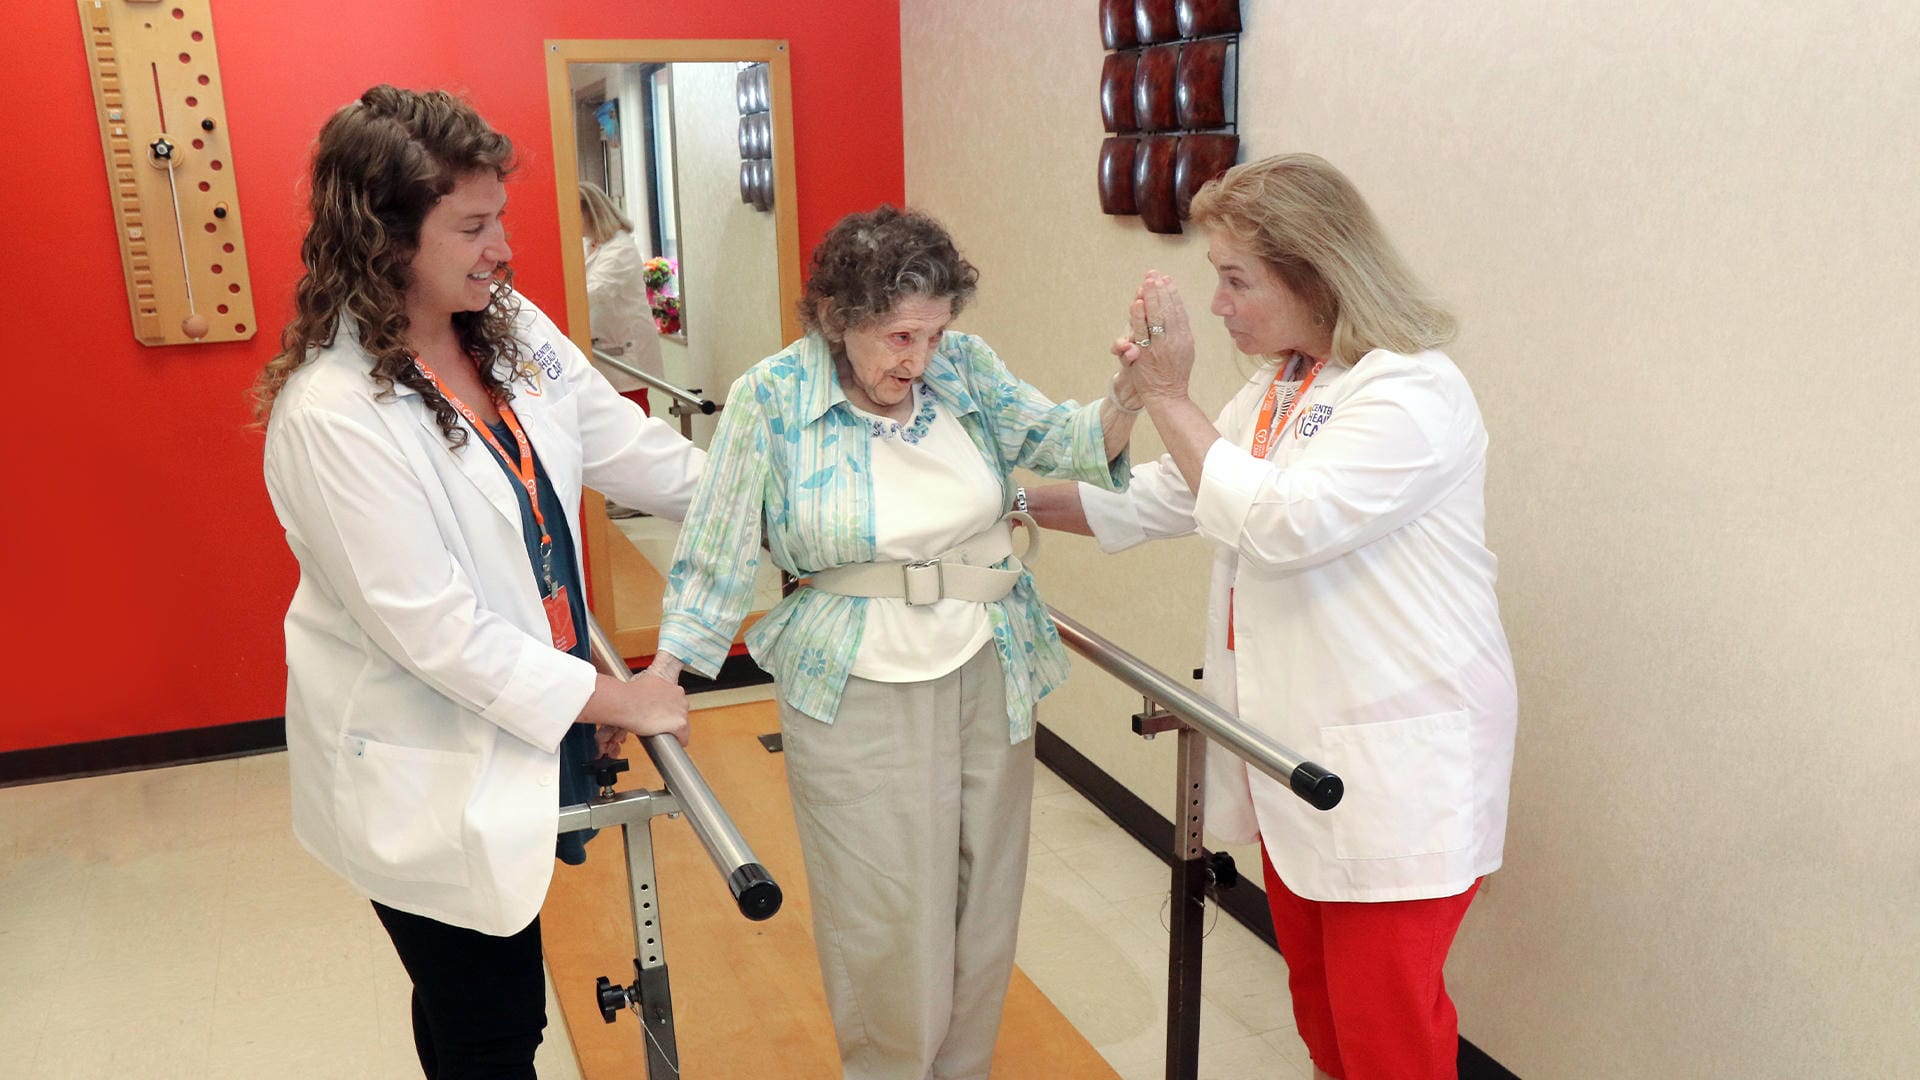
Watch the actual Tuesday. Rising from bed, turning toward a chair, reaching the bathroom after dark. Therapy can observe each job and work on the part that goes wrong. Nursing sees the version outside the gym, including the morning after poor sleep.
Feet have their own vocabulary: fire, ice, pins and needles, or that maddeningly vague “funny.” The pain scale offers one clue. Location, timing, movement, sleep and what happened after treatment fill in the rest.
Skin Changes and Wounds Cannot Wait for the Next Routine Visit
A small area of redness can become a much larger problem when mobility, circulation, nutrition or sensation is impaired. Daily skin observation is plain work, and valuable. Staff look for pressure areas, drainage, swelling, heat, odor, changes around an existing wound and new pain that does not fit the prior pattern.
Wound care is more than a dressing order. The plan may involve pressure relief, positioning, nutrition, hydration, pain control and monitoring for signs that merit prompt clinical review. Viral suppression, immune function, diabetes, vascular health and the wound itself all affect the discussion.
This is also where handoffs earn their keep. A therapist may notice that a shoe is rubbing. A nursing assistant may see that breakfast went untouched. The evening nurse may hear that the resident avoided standing because the heel hurt. Three small observations, one developing problem.
HIV Aging Care Bronx Must Leave Room for an Honest Conversation
Some older adults have spent decades learning when it felt safe to disclose an HIV diagnosis. Others were diagnosed late in life and are still working out whom to tell. A care setting does not erase either history.
Stigma-free communication begins with privacy and ordinary respect. Staff should avoid assumptions about identity, relationships, sexual history or how a person acquired HIV. Questions need a clinical reason. Explanations should use the resident’s preferred language and account for hearing, vision, health literacy and possible cognitive change. If a resident says, “Please don’t discuss this in front of my visitor,” that is a care instruction, not a social detail.
The federal warning here is blunt. Add stigma, loneliness and thin social support, and depression or cognitive trouble may deepen. Activities, peer contact, faith practices, family involvement and regular conversation can help, provided the resident chooses the terms. Forced cheerfulness has never cured isolation.
Coordinated Long-Term Support Lives in the Handoffs
Complex care generates a great deal of information. The harder part is getting the right piece to the right person before it becomes old news.
An interdisciplinary plan may include nursing, medical providers, pharmacy, rehabilitation, dietary staff, social work, activities and wound clinicians. Each discipline should know the current priorities: medication continuity, fall prevention, pain response, skin status, nutrition, mood and the resident’s goals. Brief reviews can catch contradictions. A resident may be encouraged to attend activities while therapy has documented that the trip down the hall currently causes severe fatigue.
Families and trusted supports can offer details a chart will miss, when the resident wants them involved. They may know the usual appetite or the early sign that confusion is worsening. That knowledge should still be checked against current findings rather than copied forward forever.
Care. Support. Positive Outcomes. Centers Health Care.
Care at Centers Health Care often begins in the middle of somebody’s story. Maybe a hospitalization came first. Or the map changed after a stroke. Pain can redraw it too. Rehabilitation may come in early; skilled nursing or long-term support may stay for a longer stretch.
The destination varies too. Home may still be the plan. So might a safer transfer, a protected wound, or enough comfort to make it downstairs for lunch. Some weeks move. Some wobble. Wednesday morning comes anyway.
Hope Center sits on University Avenue. Its program list includes HIV/AIDS care and long-term care. There is short-term rehabilitation, too, along with pain management, stroke care and wound care. Six service names fit neatly on a webpage. An older resident experiences them as one day, one medication pass, one sore heel and one conversation handed from shift to shift.
Our Steps to Home series follows patients through rehabilitation and the journey from hospital to home.
Our Steps to Home series follows patients through rehabilitation and the journey from hospital to home: